Q3: Can I improve my existing product
Months 1-2 (Initial Titration): Maintain weights from before starting medication Focus on consistent training despite side effects Priority is showing up, not pushing intensity If you miss workouts due to nausea, dont compensate by training harder Months 3-6 (Adaptation Phase): Attempt modest strength increases (2.5-5 pounds on upper body, 5-10 pounds on lower body every 3-4 weeks) If strength stalls, thats acceptable maintenance is success Increase reps before increasing weight (if you can do 12 reps with good form, add weight) Months 7-11 (Maintenance Phase): Continue training at maintained strength levels Accept that weight loss velocity is slowing Focus shifts to body composition refinement Consider adding 1 additional set per exercise if recovery permits MY UNCONVENTIONAL RECOMMENDATION I actually tell patients to stop tracking their one-rep maxes during Retatrutide treatment
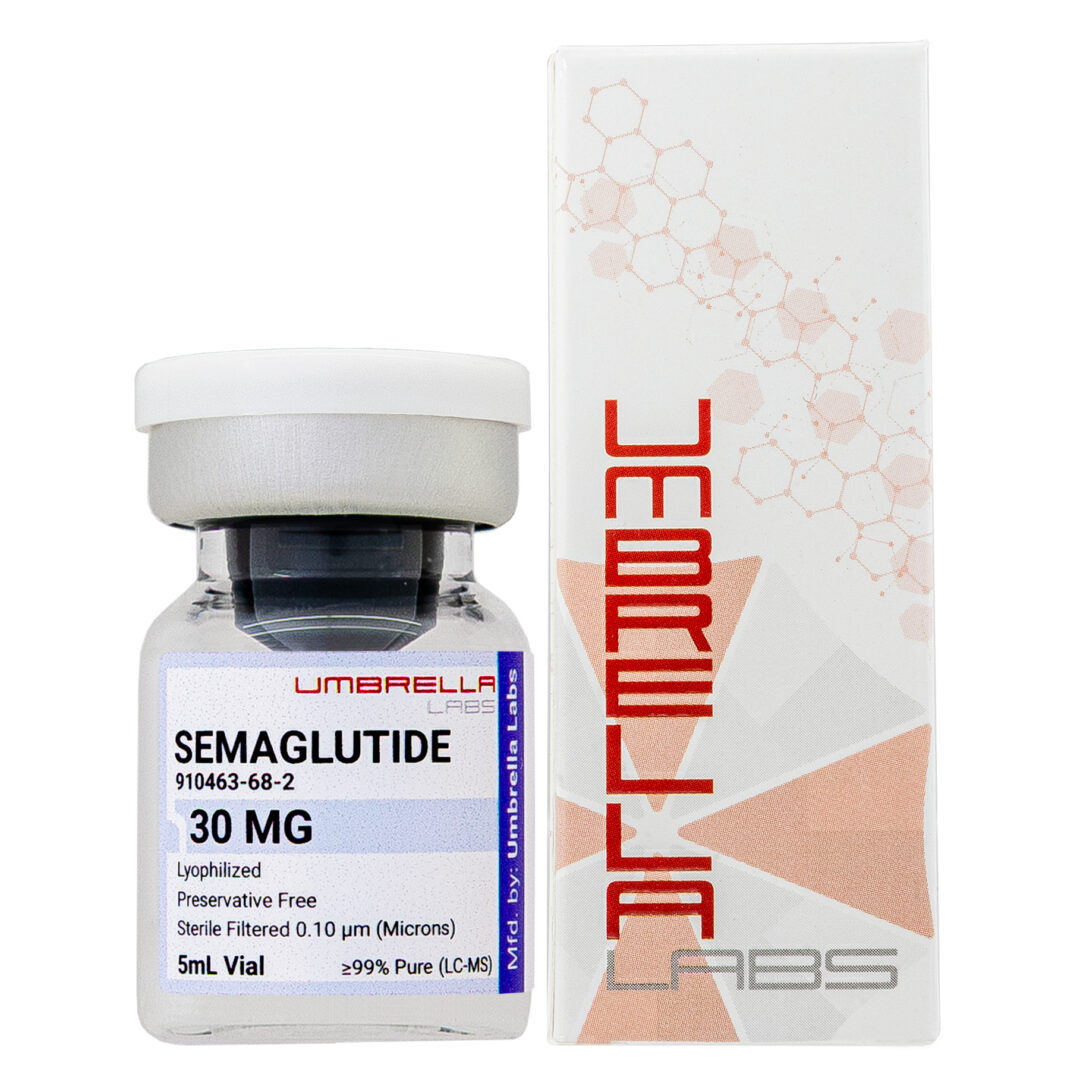
Can I get a private prescription for semaglutide in the UK
While genetic testing does not predict exact medication response, it can help providers understand metabolic predispositions and support more informed conversations about whether GLP-1 is a good clinical fit for a particular patient
But you forgot (at least) one key difference
E1 is a thiamin pyrophosphate (TPP)-dependent -ketoacid dehydrogenase, R -lipoic acid functions as a prosthetic group essential for E2 transacetylase activity, and E3 is a flavin adenine dinucleotide (FAD)-dependent dihydrolipoamide dehydrogenase ( Figure 4 )